Din aceeași categorie

Opinii şi recomandări curente pentru utilizarea meşei în chirurgia ginecologică – review al literaturii
Vitamin D (calciferol) is a biologically inactive fat-soluble vitamin with immunomodulatory and antiproliferative characteristics. Vitamin D has two functional forms: D2 (ergocalciferol) and D3 (cholecalciferol), both prohormones. To obtain its active form, 1,25-dihydroxyvitamin D3 (1,25(OH)2D3), two successive hydroxylations, made with 1-alpha-hydroxylase (1a-OHase), are required: the first in the liver and the second in the kidneys. 1a-OHase level influences the local immune system and is present in large quantities in different tissues, including the placenta and decidual tissues, indicating the importance of 1,25(OH)2D3 production for the fetal-placental unit development. Numerous studies have demonstrated that placental synthesis of 1,25(OH)2D3 is essential in implantation, placentation and fetal growth. High levels of 1a-OHase protein and expression of 1a-OHase mRNA were found in the first-trimester and second-trimester placenta and decidua(1). Decidua and trophoblast cells express vitamin D receptor (VDR) as well as 1a-OHase, suggesting an autocrine or paracrine role for 1,25(OH)2D3 within these tissues(2). The active forms of vitamin D are of major importance in the metabolism of calcium and phosphor, which means that vitamin D receptors are expressed on almost all cells of the body(3-5). During pregnancy, maternal circulating levels of 1,25(OH)2D3 double with advancing gestation age, resulting in a concomitant increase in calcium uptake by the maternal intestine(6).
Vitamin D3 exerts an autocrine/intracrine effect and control via plasma membranes ion channels, via VDR genes located near autoimmune and cancer-associated genes over normal cellular metabolism and cellular immune function(7).
The body has been shown to make up to 25,000 IU of vitamin D3 a day in response to adequate sun exposure to UVB.
Nowadays, vitamin D deficiency has become of high interest, given the accelerated increase in its incidence. To compensate for the low intake of vitamin D from UVB radiation exposure, the general population needs to procure vitamin D from foods, which generally have a low percentage. Vitamin D deficiency is increasingly common in both the general population and pregnant women and newborns; between 18% and 84% of pregnant women suffer from vitamin D deficiency(8). Vitamin D deficiency during pregnancy can manifest in two distinct forms: (1) on the pregnant woman, which can lead to pregnancy-induced hypertension, preeclampsia(9-13), preterm birth(14,15), gestational diabetes mellitus(16), recurrent miscarriages(17); or (2) on the product of conception and the fetal appendages, which can cause: decidualization(18), defective implantation, abnormal development of the fetal skeleton, large, enlarged fountains(19), low birth weight (LBW) or small for gestational age (SGA) fetus, respiratory diseases such as asthma or bronchopulmonary dysplasia, aortic supravalvular stenosis, infections, autoimmune diseases.
It is well known that, during pregnancy, the level of 1,25-dihydroxyvitamin D3 increases to an extreme, and is particularly linked to DBP (vitamin D binding protein). Usually, the level of vitamin D is directly related to Ca, phosphates and PTH serum levels. However, during pregnancy, it has been shown that they are no longer interdependent. There is evidence that, in pregnant women, a significantly increased level of vitamin D does not lead to calcium and hypercalcemia, as it does in the general population(20).
The American Institute of Medicine (AIM) and the European Food Safety Authority (EFSA) state that the value of sufficiency blood levels of 25(OH)D is above 20 ng/mL (50 nmol/L), a similar level for pregnant and non-pregnant women(21). The Institute of Medicine and Health from Canada define the value of sufficiency blood levels of vitamin D as serum 25(OH)D)>30 nmol/L(22). Moreover, the optimal level of 25-OH-D during pregnancy is not precisely known. During pregnancy, physiological changes note an increase of 50-100% in serum concentrations of 1,25(OH)2D over the non-pregnant state during the second trimester and 100% during the third trimester(23,24). The mechanism underlying the increased serum of 1,25(OH)2D concentrations during pregnancy is not clear. Parathyroid hormone, the main stimulus for increased renal hydroxylation of 25(OH)D to 1,25(OH)2D, has not been shown to increase during pregnancy. In my practice (Dr. Anca A. Simionescu), last winter (in December), I saw, in 99% of all trimester pregnancies, a vitamin D level below 15 ng/mL, wondering if the cutoff during pregnancy shouldn’t be changed. Do we need to check the vitamin D levels of healthy pregnant women?
The Canadian Paediatric Society recommends regular vitamin D supplementation during pregnancy, ranging from 200 to 400 IU/day (5 to 10 µg/day)(25). Many vitamins, minerals and supplements in pregnancy have recently added vitamin D3.
The reported effects of vitamin D on the placenta are the following: angiogenesis(26), immune function(27), inflammation (antiinflammatory) and implantation. Immune adaptations are mandatory for the proper functioning of pregnancy, and vitamin D has a significant role in implantation through its function in the inflammation and immune process. Experiments have shown that after administering 1,25(OH)2D3 in rats, a more rapid decidualization happened, and the uterus’ mass increased significantly(18). Trophoblastic cell cultures that were created in an environment similar to that of antiphospholipid syndrome by the addition of antiphospholipid antibodies showed a reduced inflammatory response in the presence of vitamin D(28).
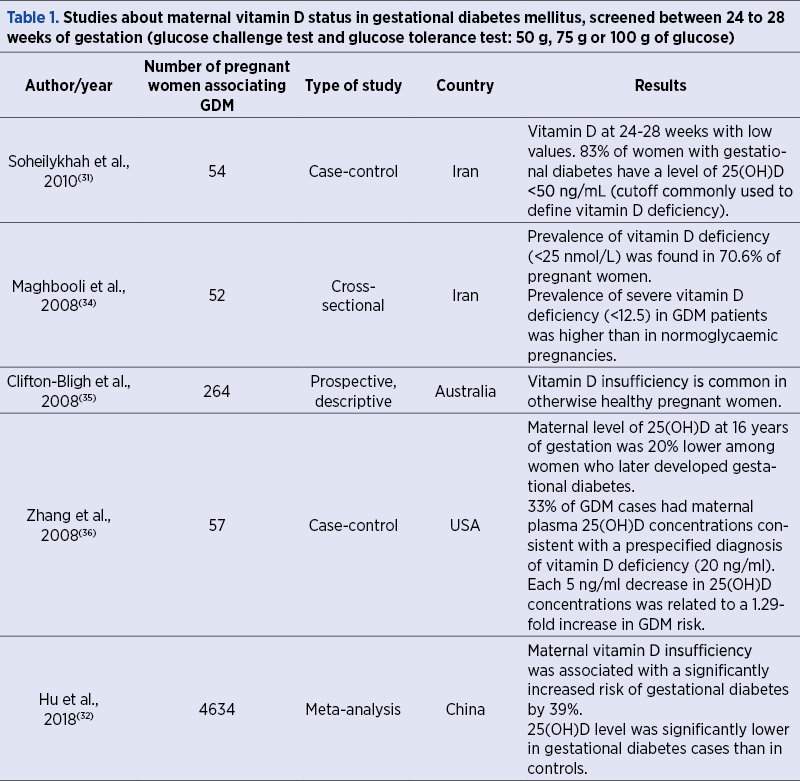
Gestational diabetes mellitus (GDM). As it was stated about 30 years ago, 1,25-dihydroxyvitamin D plays a role in regulating insulin secretion(29) and in maintaining the normal glucose homeostasis. During pregnancy, the prevalence of GDM increases simultaneously with the PTH stimulus for renal stimulation of 25-OH-D(30). Regarding the role of vitamin D deficiency in the occurrence of gestational diabetes mellitus, it has only been shown that vitamin D improves insulin sensitivity and glucose tolerance and that patients with gestational diabetes frequently experience low levels of vitamin D(31). However, it is not yet known whether taking vitamin D supplements may or may not prevent the gestational diabetes. Table 1 indicates some studies about maternal vitamin D status in diabetes mellitus, in different countries, with variable sunshine regimens. The studies demonstrate that vitamin D insufficiency is significantly associated with an increased risk of gestational diabetes(32,33).
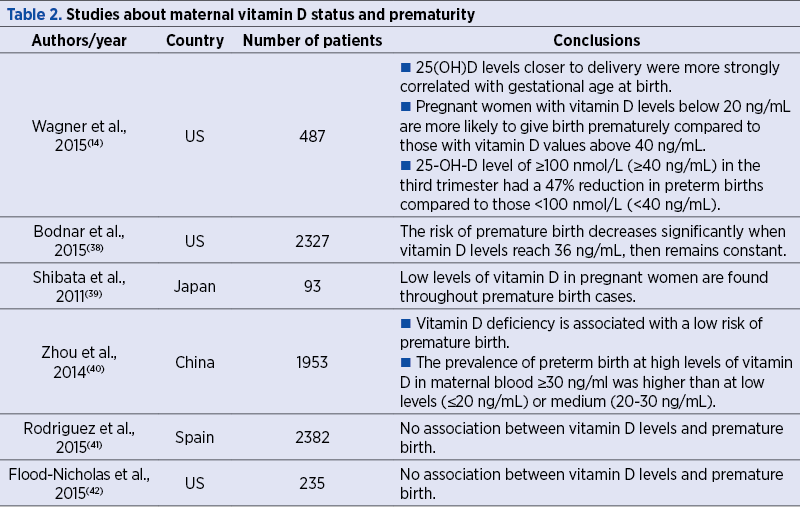
Preterm birth. While the results of the existing studies are contradictory regarding vitamin D deficiency and preterm birth or preterm birth risk, most studies conclude that there is a correlation between preterm birth and low vitamin D levels. Studies have suggested a relationship between the 25-OH-D level and the pregnancy outcome of prematurity(37); the authors have suggested a modifiable risk of prematurity through vitamin D repletion as late as the second trimester and even into the third trimester of pregnancy. The strongest association was found in twin pregnancies, where the risk of premature birth in a pregnant woman with vitamin D deficiency is stated as 60%(6).
Table 2 shows the conclusions of studies regarding the correlation between prematurity and low levels of 25-OH-D in maternal serum.
Preeclampsia. Low maternal 25-OH-D serum levels in the first trimester of pregnancy have been found in most patients developing preeclampsia. An infant born to mothers with preeclampsia has a two times higher risk of vitamin D deficiency than those born to mothers without this pathology(6,43). In these cases, the benefit to the mother, brought by the birth of the child, is weighted against the detriment of the child’s early birth and all the risks associated with premature birth.
Low birth weight (LBW) and small for gestational age (SGA). Attempts have been made to establish a relationship between LBW and SGA and vitamin D deficiency in pregnant women, but some studies have shown the opposite. Studies have shown a correlation between vitamin D treatment and the characteristics of the newborn. Khalessi et al. have found the head circumference at birth ≤33 cm associated with vitamin D deficiency, and also with LBW(44). Several studies in different populations have concluded that birth weight has not been influenced after vitamin D (and calcium) supplementation(20,45,46).
Infants level of 25-OH-D is correlated with maternal 25-OH-D level. Changes in the fetal skeleton measurements due to vitamin D deficiency may be observed around the age of 19 weeks of gestation(47). Craniotabes were associated with elevated alkaline phosphatase levels, normal PTH and with low levels of 25(OH)D. A recent systematic review and meta-analysis of randomised control trials on the effect of vitamin D supplementation on birth weight found that vitamin D supplementation alone significantly increased birth weight, but not on dose-dependent administration(48). Contradictory results were found regarding vitamin D administration and LBW or SGA babies.
The respiratory system changes are diverse, and vitamin D deficiency can lead to asthma, bronchopulmonary dysplasia (which is specific to premature infants) and respiratory infections. Bronchopulmonary dysplasia is characterized by an abnormal structure of the distal lung structures and can lead to the restriction of the development of alveoli and blood vessels that persists even after birth(49-50). In general, the interruption of physiological development occurs in the canalicular stage(51,52).
While the role of vitamin D in the normal development of the lungs has been scientifically proven(53-55), the link between vitamin D deficiency and bronchopulmonary dysplasia is still being studied. When it comes to deciding the optimal level of vitamin D for pregnant women, there are two opinions: 20 ng/ml indicated by the Institute of Medicine, while the Endocrine Society recommends around 30 ng/ml or more. These estimates were made after measuring vitamin D levels in a tribe from Africa where vitamin D levels reached 46 ng/ml and 60 ng/ml for pregnant women. After considering the different climatic conditions, Hollis et al. suggested a minimum normal value for the pregnancy rate of 40 ng/ml(20). Thus, the recommended daily doses are 4000-10,000 IU (National Institute for Health and Clinical Excellence, UK)(56).
In conclusion, it remains to validate whether the measurement of vitamin D levels and vitamin D supplementation (and calcium) during pregnancy should be recommended. Further studies are recommended to demonstrate if there is any connection between the 25-OH-D level and maternal and fetal complications, and to specify when and how vitamin D level should be dosed.
Conflict of interests: The authors declare no conflict of interests.

Un studiu relevă o corelaţie între statusul ponderal şi carenţa de vitamină D
Un studiu intern realizat în cadrul unei clinici din Bucureşti a evidenţiat niveluri alarmant de scăzute ale vitaminei D în rândul pacienţilor, în urma analizei de laborator 25-OH-vitamina D. Studiul a fost desfăşurat în perioada 2022-2023,...
Studiu. Peste 82% din pacienţii cu COVID-19 au deficienţă de vitamina D
Peste 82% din pacienţii care suferă de COVID-19 au o lipsă de vitamina D, iar această insuficienţă este mai frecventă la bărbaţi, potrivit unui studiu publicat în Journal of Clinical Endocrinology & Metabolism, relatează EFE....