Din aceeași categorie

Introduction
Pediatric autoimmune hepatitis (AIH) is a form of chronic hepatic disease of uncertain etiology, characterized by hepatic cytolysis, circulating autoantibodies and/or increased levels of IgG. AIH is responsible for approximately 2-5% of the chronic liver diseases in children, but these numbers increase every year due to enhanced awareness and to an actual increase of the incidence(1,2).
The spectrum of pediatric autoimmune liver disease includes three disorders that present autoimmune mechanisms: autoimmune hepatitis (AIH), autoimmune sclerosing cholangitis, and de novo AIH post-liver transplantation. AIH is divided into two types, based on the autoantibody profile: type 1 (AIH-1), with positive anti-nuclear antibodies (ANA) and/or anti-smooth muscle antibodies (SMA), and type 2 (AIH-2), with positive anti-liver kidney microsomal type 1 antibody (anti-LKM1) and/or anti-liver cytosol type 1 antibody (anti-LC-1)(1). Autoimmune sclerosing cholangitis (ASC) is an overlap syndrome between AIH-1 and sclerosing cholangitis, characterized by inflammation and stenosis of the bile ducts and associated with the presence of autoantibodies, ANA, antineutrophil cytoplasmic antibody (ANCA) in more than 80% of patients, and SMA in more than 60% of patients. ASC and AIH may be associated with inflammatory bowel disease (IBD). For the differential diagnosis of ASC and AIH-1, magnetic resonance cholangiopancreatography (MRCP) should be used, as the autoantibody profiles are very similar(1,3).
The clinical presentation of AIH is very heterogeneous, including acute onset resembling viral hepatitis with nonspecific symptoms, acute liver failure (ALF) with hepatic encephalopathy, insidious onset lasting few months to few years until diagnosis, onset with complications of cirrhosis and portal hypertension or incidental finding without any symptoms(1).
Case report
We report the case of a 7-year-old girl, who was admitted in our department for the investigation of increased transaminases, discovered incidentally, the values exceeding three times the upper normal limit. The elevated transaminases were firstly observed three years before admission.
At the moment of admission, the patient had no symptoms. The physical examination revealed a well-nourished girl with a weight of 19 kg and a height of 119 cm. She had normal colored skin, normal cardiovascular and respiratory examination, respiratory rate 18/min, heart rate 70/min, without hepatosplenomegaly. The laboratory analyses revealed increased transaminases (aspartate aminotransferase, AST 99 IU/L, alanine aminotransferase, ALT 92 IU/L), without cholestasis. The coagulation (prothrombin time and INR) and serum albumin level were within normal limits. The serologies for hepatitis A, B, C, cytomegalovirus infection, Epstein-Barr virus infection, and herpes simplex virus were negative. Alpha-1 antitrypsin (A1AT) deficiency and Wilson’s disease (WD) were excluded due to the normal level of A1AT, ceruloplasmin, and 24-hour urinary copper excretion.
The serum level of the IgG was normal, but she presented IgA deficiency (11 mg/dl). ANA (1:80) and SMA (1:320), performed by immunofluorescence, were positive. Given the possible association of AIH with other autoimmunities (in 20% of the cases), we excluded autoimmune thyroiditis (normal TSH and fT4, negative thyroid peroxidase antibodies) and coeliac disease (negative antitransglutaminase IgA and IgG antibodies). The abdominal ultrasound revealed a normal homogeneous echotexture of the liver and a normal spleen size. MRCP was not performed. Also, we could not perform the liver biopsy due to the refusal of the parents. Transient elastography of the liver (Fibroscan) indicated the absence of fibrosis (F0 Metavir). Based on the laboratory findings, we established the diagnosis of AIH-1 and we initiated the treatment with prednisone at a dose of 1 mg/kg/day. The evolution was rapidly favorable, with decreasing transaminases after two weeks. After six weeks of treatment, the transaminases were within the normal range, and then we reduced the prednisone dose to the maintenance dosage of 5 mg/day. The transaminases remained within normal limits.
Discussion
AIH is a progressive inflammatory process of the liver, which can evolve unfavorably without proper treatment. AIH occurs within all ethnic groups, but the clinical manifestations vary with race and ethnicity. Alaskan natives have more frequently icteric AIH, Hispanics more commonly present with cirrhosis, and African Americans have accelerated disease progression. The estimated incidence for pediatric AIH varies from 0.23 to 0.4 per 100,000 person-years. In the past years, there has been an almost 50% increased in incidence in Western European countries(4).
The clinical manifestations of AIH in children vary from ALF, insidious onset with nonspecific manifestations (fatigue, abdominal pain, jaundice, headache), onset with complications of cirrhosis, or incidental finding of increased hepatic aminotransferases(1,5). This last category of the accidental discovery of elevated transaminases, including the case of our patient, constitutes less than 5% of the patients diagnosed with AIH in retrospective studies. Still, the actual prevalence cannot be accurately estimated(1,6). Most children with AIH have clinical signs of underlying chronic liver disease, including cutaneous stigmata (spider naevi, palmar erythema, leukonychia, striae), firm liver and splenomegaly. The course of the disease can be fluctuating, with flares and spontaneous remissions, a pattern that may result in delayed referral and diagnosis(6).
The most representative features of AIH are the female predominance (75%), hypergammaglobulinemia (IgG), circulating autoantibodies and interface hepatitis on biopsy(7,8). However, in 15-25% of the patients, IgG serum levels can be within normal limits, as in our patient. Also, IgA deficiency is present frequently in AIH-2, in almost half of the patients, unlike AIH-1, with only 7%(1,6,8). IgA deficiency has long been associated with several autoimmune diseases, especially coeliac disease, rheumatoid arthritis and systemic lupus erythematosus(9).
The clinical manifestations and the treatment are similar in both types, but there are some differences in prevalence and prognosis. AIH-1 is most frequent in adolescents and young adults, while AIH-2 presents at a younger age, including infancy. Regarding the disease prognosis, AIH-2 evolves more frequently with ALF, and the remission is challenging to be induced and maintain(1).
The autoantibody cut-off differs in children from adults. A lower titer is considered positive in children: >1:20 for ANA, >1:10 for SMA, and any titer are significant for anti-LKM-1(1,10,11). Anti-LKM-1 are positive in less than 5% of patients with chronic hepatitis C and AIH-1. Autoantibodies profiles for AIH-1 and AIH-2 can appear simultaneously in very rare cases(1,10). Our patient has features from both subtypes. The positive autoantibody profile (ANA, SMA), the mild evolution (possible evolving for three years without any clinical manifestations) and the rapid response to treatment support the AIH-1 type. In contrast, the young age of onset, IgA deficiency, and positive anti-LKM-1 are frequently present in AIH-2.
In both types of AIH, there is often a positive family history for other autoimmune diseases. Approximately 20% of AIH patients develop another autoimmunity such as thyroiditis, coeliac disease, IBD, hemolytic anemia, idiopathic thrombocytopenia, glomerulonephritis, hypoparathyroidism, insulin-dependent diabetes or vitiligo. It is essential to actively search for these conditions on follow-ups for prompt treatment(1,12). There was no family history of autoimmunity in our patient, and we did not find other autoimmune disorders associated.
The diagnosis of AIH is based on clinical, biochemical, immunological features and on histological changes. It is necessary to exclude other causes (viral hepatitis B, C, WD, nonalcoholic steatohepatitis and drug-induced lived disease)(1).
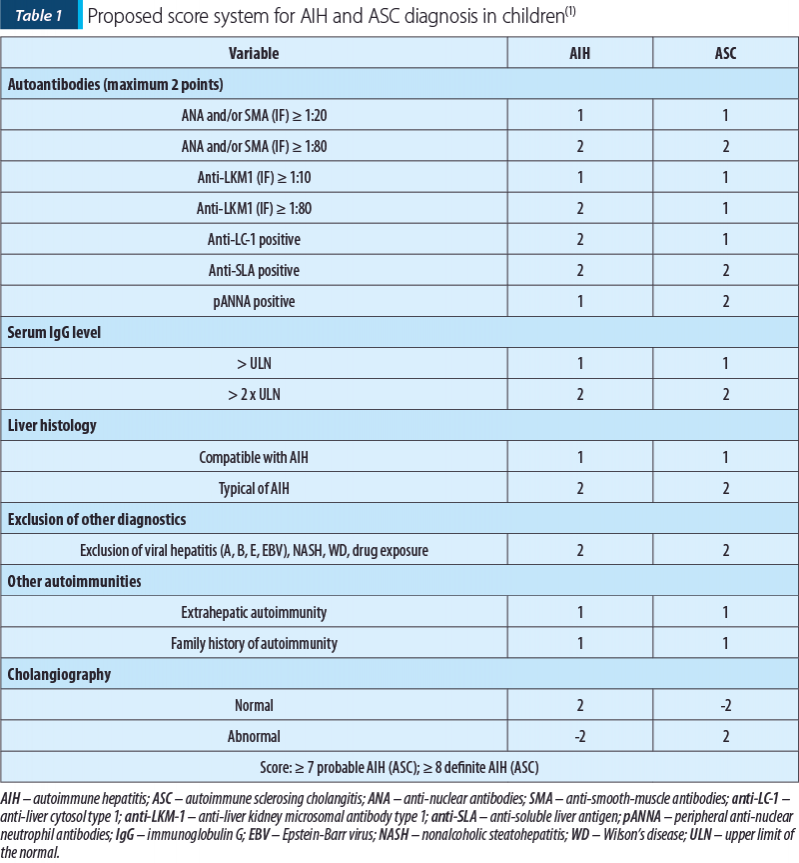
A scoring system was proposed by the International Autoimmune Hepatitis Group (IAIHG)(7). This score includes clinical, immunological and biopsy criteria, excluding other causes of liver damage. It can also include HLA haplotype, the association of another autoimmunity, and response to treatment to classify AIH as possible or defined. However, this scoring system was designed for research purposes and is unsuitable for pediatric AIH(1,7). The IAIHG scoring system was revised in 2008, when a more simplified version was proposed for clinical use in AIH diagnosis. However, this score did not include either MRCP, therefore it is not suitable for diagnosing overlap syndromes since they cannot differentiate ASC from AIH(13-15). Given the need for a proper scoring system applicable for pediatric diagnosis of AIH and ASC, ESPGHAN proposed a scoring system that includes cholangiography alongside positive autoantibodies, IgG level, liver biopsy, exclusion of other causes of hepatitis, and association of other autoimmunities (Table 1)(1). MRCP was proven to have a high sensitivity (84%) and accuracy (84%), and it is recommended as the investigation of choice for the evaluation of biliary diseases in children(16). Recently, a score for pediatric AIH was proposed, including autoantibodies (0-2 points), hypergammaglobulinemia, exclusion of viral hepatitis and WD (1 point each), and liver histology (3 points), associated with a normal cholangiogram. A score ≥6 had a sensitivity of 95.8% and a specificity of 100% for AIH diagnosis, with an area under the receiver operating characteristic curve of 97.1%(17).
Although it has a high sensitivity (up to 95%), we could not apply this score for our patient, due to the lack of hepatic biopsy and cholangiography. A scoring system could be helpful for the diagnosis of AIH but, given the heterogeneity of these cases, not meeting the criteria does not exclude the diagnosis in a particular patient.
The treatment for AIH-1 and AIH-2 consists of immunosuppressive agents regardless of liver impairment. The first-line treatment consists of prednisone or prednisolone in a dose of 2 mg/kg (maximum of 60 mg/kg), which is gradually decreased in a period of 4 to 8 weeks, in concordance with the decrease of transaminase levels, to a maintenance dose of 2.5-5 mg/day. The response rate varies between 60% and 90%. Remission is defined as transaminase levels in the normal range, normalization of IgG levels, negative or very low autoantibody titer, or the histological resolution of the inflammation(1,18). Our case had a good evolution on prednisone alone. The second immunosuppressive drug used in AIH is azathioprine. Two ways of initiating azathioprine treatment are accepted: together with prednisone from the beginning or added in the presence of serious steroid side effects, or if the transaminase levels stop decreasing on prednisone alone. The azathioprine treatment is started with 0.5 mg/kg/day and can be increased to 2-2.5 mg/kg if signs of toxicity are not present. About 85% of patients require azathioprine association in the treatment(1). The immunosuppressive therapy duration is not clearly defined, but the recommendations are for at least three years of biochemical remission before beginning a gradual withdrawal to ensure histological resolution. Liver transplantation represents an option for unresponsive patients, end-stage chronic liver disease and ALF, but the posttransplant recurrence is frequent, despite immunosuppressive therapy, especially in ASC patients(1,19).
For our patient, we expect a favorable evolution due to the rapid response to treatment. We hope to be able to maintain the remission with a low dose of prednisone.
Conclusions
We reported a patient diagnosed with AIH-1 with no clinical manifestations, presenting only an increase of transaminases with normal IgG and IgA deficiency, with positive ANA, anti-SMA, and also anti-LKM-1 autoantibodies. This case emphasizes the importance of considering AIH diagnosis in any child with elevated transaminases, regardless of age and symptoms, given that the incidence of this disorder is rapidly increasing.
hepatită autoimunăcopilasimptomaticautoanticorpidiagnostic
Conf. dr. Adrian Pană: „Avem nevoie de un algoritm validat pentru identificarea tumorilor desmoide”
Una dintre principalele provocări în gestionarea tumorilor desmodide este lipsa unui cod de diagnosticare specific, fapt ce face ca aceste cazuri să fie subdiagnosticate în țara noastră, a atr...

INSP: în 2025 au fost raportate 12.173 de cazuri noi de Alzheimer
Tema din 2026 evidențiază importanța recunoașterii timpurii a semnelor și simptomelor demenței.
...
Îngrijirea mamei și nou-născului, în centrul unui proiect cu finanțare europeană
Îngrijirile acordate mamelor și nou-născuților din grupurile vulnerabile ar urma să se îmbunătățească datorită unui proiect derulat de Institutul Național pentru Sănătatea Mamei și Copilului București.
...