Din aceeași categorie
Laryngeal cancer is one of the most common head and neck malignancies, representing 40% of all cases, and it is correlated mainly with smoking and alcohol, but also with low immunity, HPV infections, diet, and family history(1).
More than 90% of laryngeal cancers are squamous cell carcinomas, but other histological forms are described: adenocarcinomas, sarcomas, neuroendocrine carcinomas, or undifferentiated carcinomas(2).
Depending on the location of the lesion, the laryngeal cancer can be classified as:
Glottic carcinoma: it involves the true vocal folds (vocal fold and 1 cm inferiorly) in 50-60% of cases;
Supraglottic carcinoma: confined to the supraglottic area, laryngeal surface of epiglottitis, aryepiglottic fold, arytenoids, vestibule in 30-40% of cases;
Subglottic carcinoma: it extends or arises more than 10 mm below the free margin of the true vocal fold up to the inferior border of the cricoid cartilage;
Transglottic carcinoma: it originates from the center of ventricle where it spreads to the transglottic region (it crosses the ventricle from the supraglottic area to involve the true and false vocal folds or involves the glottis and extends subglottically more than 10 mm or both). There are fundamental differences between transglottic carcinoma and transglottic invasion of laryngeal carcinoma in the late stage of the lesion(2,3).


Laryngeal cancer staging
Initial evaluation of the primary tumor is based on a thorough history and combination of inspection, palpation, indirect mirror examination, or direct endoscopy. A fiber optic laryngoscopy and panendoscopy under anesthesia should generally be performed to take biopsies for a tissue diagnosis and to determine the clinical extent of the local disease(4). To evaluate the degree of local infiltration, the presence of regional lymph nodes and distant metastases or second primary tumors, CT, MRI and PET/CT are used. Computed Tomography can identify cervical lymph nodes metastasis and evaluate the bone cortex invasion and destruction. MRI allows a better discrimination of tumor from healthy tissues, perineural spread and cartilage invasion identification, particularly for non-ossified cartilages, but, unlike CT-scan, it does not show precise bony details(5).
The Positron Emission Tomography (PET) commonly uses 2-deoxy-2fluoro-(F-18)-D-glucose (FDG), an analogue of glucose that accumulates itself unspecifically in all glucose-dependent tissues, hence FDG uptake reflects metabolic activity of tumor lesions. The value of 18F-FDG uptake (Standardized Uptake Values, SUVs) depends mainly on tumor histology, proliferation and tissue hypoxia(6). PET-CT appears to be at least as sensitive and specific as CT and MRI in detecting primary head and neck tumors, but superior for detecting regional nodal metastases, as well as distant metastases and second primary tumors(7-9).Therefore, PET scan should be considered in patients at high risk for metastatic disease or with equivocal findings on CT or MRI scan, and also can be indicated for patients at increased risk of second malignancy (especially those with a smoking history) who will not have an operative panendoscopy (laryngoscopy, esophagoscopy, bronchoscopy)(10,11).
Staging depends on tumor location in one of the three anatomical regions: the glottis (true vocal cords, anterior and posterior commissures); the supraglottis (epiglottis, arytenoids and aryepiglottic folds, and false cords); and the subglottis. The term advanced laryngeal cancer generally denotes stage III or IV according to the Union for International Cancer Control (UICC)/American Joint Committee on Cancer (AJCC) staging system(3).
Stage III is represented by T3 or N1 tumors.
A T3 tumor is a tumor that remains limited to larynx but invades adjacent anatomical laryngeal regions, possibly causing vocal cord fixation. Independently of the initial tumor location (glottis, the supraglottis or subglottis), the fixation of the vocal cords always defines a T3 tumor, corresponding to deeply invasive lesions. The cervical lymph nodes are classified N1 if the metastasis is clinically detected in a single ipsilateral lymph node and the maximum diameter does not exceed 3 cm.
The non-metastatic stage IV includes N2-N3 or T4 tumors.
The metastatic lymph nodes are classified as N2 in case of lymph node 3 to 6 cm in its greatest dimension (N2a: single and ipsilateral, N2b: multiples and ipsilateral and N2c: bilateral or contralateral lymph nodes) and as N3 for more than 6 cm in the greatest dimension. Regarding the tumor classification, the T4a tumor invades through the thyroid cartilage and/or invades the tissues beyond the larynx (trachea, soft tissues of neck, including deep extrinsic muscle of the tongue, strap muscles, thyroid, or esophagus) and a T4 b tumor invades prevertebral space, encases carotid artery, or invades mediastinal structures.
Due to the importance of the larynx’s functions, advanced laryngeal cancer and its treatment are associated with significant morbidity and mortality, with important detrimental effect on the quality of life for the patient and increased financial costs for society.
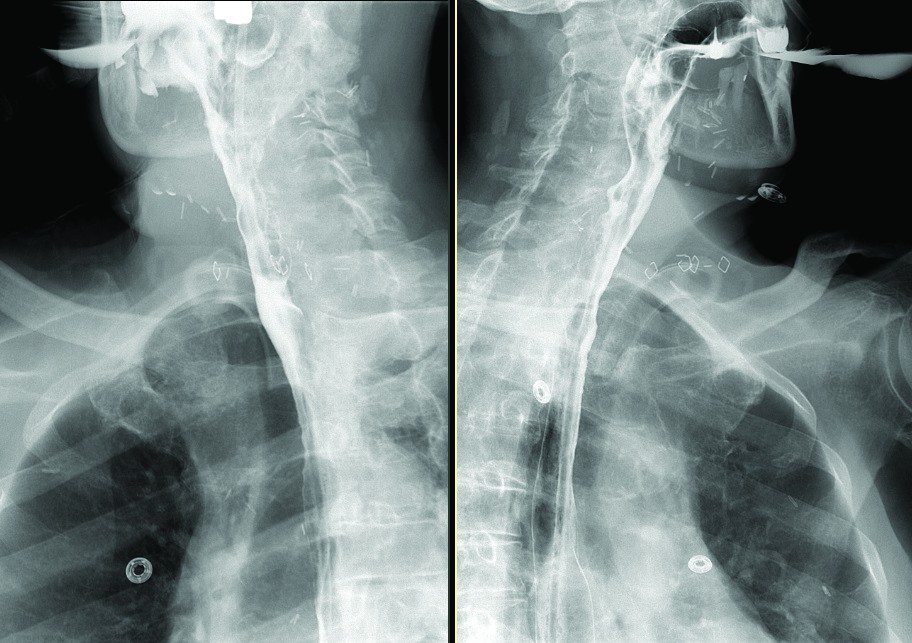
Treatment strategy
The management of the advanced laryngeal cancer is complex and should be established by a multidisciplinary tumor board. The main goals are local control and survival, but also the functional organ preservation (speech, swallowing and airway patency), if possible. The main decision factors for the therapeutic strategy are: the patient-specific factors (age, performance status, comorbidity, psychosocial support), the cancer topography and staging, but also the physician expertise and the availability of rehabilitation services(12,13).
There are two major therapeutic strategies:
a) Total laryngectomy associated with adjuvant radio and chemotherapy.
b) Larynx preservation, including neoadjuvant chemotherapy followed by exclusive radiotherapy or concurrent radio-chemotherapy or radio-biotherapy.
A) Open Total Laryngectomy
Total laryngectomy, the surgical removal of the larynx with definitive tracheal stoma, remains the initial treatment choice for locally advanced laryngeal cancer.
Tumor surgery
Total laryngectomy is appropriate for patients that may not recover vocal or respiratory function if a larynx-preservation therapy is performed or for older and/or fragile patients, with poor compliance and functional status who do not fit for chemo-radiotherapy because of important risk for major toxicities.
The main surgical technique is the cranio-caudal laryngectomy. Retrograde laryngectomy is preferred for glottic or supraglottic tumors because it eliminates the risk of trans-tumoral laryngeal resection and ensures an adequate suprahyoid resection margin(14,15).
The total laryngectomy ensures protection against aspiration, easier swallowing and the possibility to speak with the help of a tracheoesophageal prosthesis. Its main disadvantage is the permanent tracheostomy. The laryngectomy is an absolute indication for:
1) tumors with cartilage destruction and anterior spread outside the larynx;
2) posterior commissure or bilateral arytenoid joint involvement;
3) circumferential submucosal disease;
4) subglottic extension with extensive invasion of the cricoid cartilage.
The neck dissection depends on cervical lymph nodes involvement and can be prophylactic, for early NO/N1 stages, or radical neck dissection for more advanced N2/N3 stage, and can be ipsilateral (in glottic carcinoma) or bilateral (supraglottic, medial wall of pyriform fossa, bilateral glottis carcinoma). According to the Committee for Head and Neck Surgery and Oncology of the American Academy of Otolaryngology - Head and Neck Surgery, the cervical lymph nodes dissections are classified in:
Radical neck dissection, the standard procedure, it means the removal of lymph node levels I-V, sternocleidomastoid muscle, spinal accessory nerve, and internal jugular vein.
Modified neck dissections
a) extended radical dissection: removal of additional lymph node or non lymphatic structures (retropharyngeal lymph nodes, hypoglossal nerve, portions of the prevertebral musculature, or the carotid artery);
b) modified radical dissection: preservation of non lymphatic structures - spinal accessory nerve, internal jugular vein, and/or sternomastoid muscle;
c) selective dissection: preservation of lymphatic structures - one or more lymph node groups normally removed in a radical neck dissection are preserved, in order to keep intact the anatomical and functional state, and minimize the risks of cervico-facial lymphedema(16).
Total laryngectomy complications
The complications of total laryngectomy are classified in immediate and long term complication. Acute complications are represented by bleeding, hematoma, seroma, wound dehiscence or infection, lymphatic fistulas, pharyngotracheal or pharyngocutaneous fistulas. Long term complications are mainly stomal stenosis, pharyngoesophageal stenosis, cervico-facial lymphedema (in radical neck dissection), hypothyroidism, voice and loss of smell(14).
B) Minimally invasive surgery techniques
To avoid a wide surgical field and reduce the local morbidity, two transoral techniques have been developed:
B.1) Transoral robotic surgery (TORS), introduced in clinical practice in 2007, adapted the open technique surgical steps to an endoscopic approach, permitting the direct intraoral view in order to achieve a maximal mucosa - sparing resection with minimal pharyngotomy defect and limiting the lateral exposure of the cervical vessels(17).
As a rule, the application of transoral surgery should never compromise the ability to completely remove the tumor, the issues of concern including prior tracheotomy, severe soft tissue fibrosis and adequate evaluation of the cervical lymph nodes(18).
B.2) Transoral Endoscopic Ultrasonic Total Laryngectomy (TOUSS-TL) is a transoral, endoscopic but non-robotic approach possible only for patients with laryngeal cancer without indication for neck dissection and no invasion through the thyroid cartilage or soft tissues of the neck (T4a) or major extralaryngeal invasion (T4b)(19).
Recurrence after total laryngectomy
The recurrence can be local, to the resection site, nodal, to cervical lymph nodes, or distal, the lung being the most common site of recurrence as a distant metastasis. The median time of recurrence following laryngectomy is 13.3 months, more rapid for nodal recurrence (median: 9.4 months) than for local recurrence (median: 12 months). Lung metastases had the longest time to recurrence (median: 20 months)(20). The main three factors associated with an increased risk of locoregional recurrence after surgery are tumor stage (T3-T4 tumors), lymph nodes stages (two or more positive lymph nodes and/or extracapsular extension) and surgical margins (positive or close resection margins)(21,22). Preoperative tracheostomy, correlated with advanced tumor stage, is a significant risk factor for local recurrence. With regard to pattern of local recurrence, stomal recurrence is correlated with preoperative tracheostomy and pathological nodal status, whereas positive margins are significant risk factors for pharyngeal recurrence(23).
Adjuvant treatments
The aim of adjuvant treatment is to improve locoregional control and survival by eradicating microscopic remains of cancerous cells.
A) Adjuvant radiotherapy
A retrospective analysis on 8795 patients with lymph node-positive head and neck carcinoma (Surveillance, Epidemiology, and End Results database) treated either with surgery alone or surgery and radiotherapy between 1988 and 2001 shows that adjuvant radiotherapy improves the 5-year overall survival (from 33.4% to 43.2%; p<0.001) and cancer-specific survival (from 42.1% to 50.9%, p<.001). Adjuvant radiotherapy is a significant predictor of improved survival, resulting in an approximately 10% absolute increase in 5-year cancer-specific survival and overall survival for lymph node-positive patients compared with surgery alone(24).
B) Adjuvant chemo-radiotherapy
B.1) Sequential adjuvant chemo-radiotherapy
The Intergrup Study 0034 randomizes 442 patients with completely resected head and neck tumors between chemotherapy followed by postoperative radiotherapy or postoperative radiotherapy alone. The study included 127 patients with laryngeal cancer, 61 in the radiotherapy arm and 66 in the combination arm. The chemotherapy consisted on three cycles of Cis-platinum 100 mg/m2 on day 1 and infusion 5-FU 1 g/m2 over 24 hours on days l-5. This chemotherapy regimen was administered every 21 days. The radiation therapy was the same on each arm, 50-54 Gy delivered to “low risk” volumes and 60 Gy to “high-risk” volumes (the surgical margin was 5 mm or less, in presence of extra capsular nodal extension, and/or carcinoma in situ at the surgical margins). The association of chemotherapy to adjuvant radiotherapy produces a significant benefit in term of lymph node failure (decrease from 10% to 5%) and distant metastases (from 23% to 15%), but without significant benefit for the 4-year overall survival (44% on the RT arm versus 48% on the CT/RT arm) or disease-free survival (38% on the RT arm compared to 46% on the CT/RT arm). In terms of toxicity, the chemotherapy was well tolerated and did not affect the ability to deliver the subsequent radiotherapy(25).
B.2) Concomitant adjuvant chemo-radiotherapy
1) Cisplatin-based chemo-radiotherapy. Two prospective phase III clinical randomized trials have demonstrated that adjuvant cisplatin-based chemotherapy associated with radiotherapy improves local control compared with the same radiotherapy used alone in patients with poor prognosis of head and neck carcinomas, including advanced laryngeal cancer
European Organisation for Research and Treatment of Cancer (EORTC) 22931 study
From February 1994 to October 2000, 334 patients with high-risk head and neck cancers (oral cavity, oropharynx, larynx, or hypopharynx) treated by surgery were randomized between radiotherapy alone (38 laryngeal cancer patients included) or radiotherapy combined with concomitant cisplatin chemotherapy (37 laryngeal cancer patients included). All patients received the same postoperative radiotherapy, 54 Gy in 27 fractions to the primary site and all draining lymph nodes at risk and 66 Gy in 33 fractions to the regions that were at high risk for malignant dissemination or had inadequate resection margins. For the experimental arm, the chemotherapy consisted of 100 mg/m2 of Cisplatin on days 1, 22, and 43 of the course of radiotherapy. The results at 5 years show that concomitant chemoradiation significantly improves the progression-free survival from 36% to 47% and the overall survival from 40% to 53%(26).
Radiation Therapy Oncology Group (RTOG) 95-01 study
Between 1995 and 2000, 459 patients with high-risk head and neck cancers (oral cavity, oropharynx, larynx, or hypopharynx), totally resected, were randomly assigned to receive radiotherapy alone or in combination with concurrent Cisplatin (100 mg/m2) on days 1, 22, and 43. There were 12 patients with laryngeal cancer in the radiotherapy arm and 13 in combination therapeutic arm. The radiotherapy began as soon after surgery as adequate healing had occurred, 4-6 weeks after the surgical procedure, and delivered 60 Gy in 30 fractions with or without a boost of 6 Gy in 3 fractions to high-risk sites. The study proves that combined treatments significantly improve the locoregional control from 72% to 82% at 2 years, but that overall survival does not differ significantly(27).
Regarding toxicity, it was found that Cisplatin-based chemotherapy doubles the incidence of grade 3 or greater acute adverse effects (from 21-34% to 41-77%), in the RTOG study - four patients who received combined therapy died as a direct result of the treatment. A meta-analysis of the RTOG and EORTC trials identifies the patients who benefited significantly from the addition of chemotherapy to the radiation therapy, namely the patients with positive resection margins and/or nodal extracapsular extension(28).
2) Mitomycine C-based chemotherapy. There are two prospective phase III clinical randomized trials that used Mitomicyne C-based chemotherapy to compare the potential benefit in adjuvant setting in combination with external radiotherapy.
In a Slovenian prospective randomized clinical trial, 114 patients with stage III or IV squamous cell head-and-neck carcinoma were randomized to receive postoperative radiotherapy alone (two-dimensional, 2 Gy daily dose, 5 times weekly up to a total dose 56-70 Gy) or in combination with simultaneous Mitomycin C (15 mg/m2) and Bleomycin (5 mg twice a week) during the radiation therapy. There were 12 laryngeal cancer patients included in the radiotherapy arm and 14 in the combination arm. The radiochemotherapy group had better locoregional control (86% versus 69%, p=0.037), disease-free survival (76% vs. 60%, p=0.099) and overall survival (74% vs. 64%, p=0.036) compared with the radiotherapy alone. The association of chemotherapy increased the acute toxic effects, especially mucositis (grade 4 in 17 patients compared with only 1 for radiotherapy alone), but also dermatitis and infection, that were more frequent for these patients(29).
Yale Mitomycin Randomized Trials analyzed 195 eligible patients randomized to receive radiation therapy with or without Mitomycin (trial 1) or Mitomycin/Dicumarol (trial 2). There were 13 laryngeal cancer patients allocated in the radiotherapy arm, and 14 in the combination arm. The radiotherapy, identical for the two arms, delivered a total dose of 60-66 Gy with 1.8-2 Gy daily fraction, 5 days a week. The Mitomycin C was administered intravenously at a dose of 15 mg/m2 following radiation on the fifth day of the radiotherapy course. In the second trial, patients receiving Mitomycin also received a total of 500 mg of Dicoumarol (an anticoagulant similar to warfarin) administered orally, with 300 mg given the day before Mitomycin C and 200 mg given on the day of Mitomycin C. The trial conclusion is that concomitant administration of Mitomycin C with radiation therapy significantly improves the 5-year disease-free survival from 44% to 67% (p<.03), but without a 5-year overall survival benefit (56% vs. 41%). Hematologic toxicities were more frequently noted in the drug-treated arms, but were acceptable with no drug-related treatment deaths(30). Thus, due to its toxicity, Mitomicyn C cannot be routinely recommended in association with radiotherapy for head and neck cancers.
3) Cetuximab-based systemic treatment
Cetuximab, a monoclonal antibody targeting the epidermal growth factor receptor (EGFR), is an effective anti-neoplastic molecule that also plays a role in increasing radiosensitization(31,32). Cetuximab initial dose is 400 mg/m2 administrated intravenously (i.v.) over 120 minutes followed by cetuximab, 250 mg/m2 intravenously (i.v.) over 60 minutes on a weekly schedule(33).
Cetuximab as adjuvant for patients with intermediate-risk pathologic features
In order to evaluate whether the addition of cetuximab to radiation therapy improves overall survival in postoperative patients with intermediate risk pathologic features, RTOG opened a randomized phase III trial (RTOG 0920) that compared 60 Gy/30 fractions with the same radiotherapy associated with concomitant and adjuvant Cetuximab. The intermediate risk factors are perineural invasion, lymphovascular invasion, single lymph node >3 cm or ≥2 lymph nodes (all <6 cm) (but without extracapsular extension), close surgical margin(s) or pT3/T4a primary tumors. The results are not available yet(34).
Cetuximab as adjuvant for patients with high-risk pathologic features
The addition of concurrent chemo-radiotherapy with Cetuximab in the postoperative treatment of patients with squamous cell carcinoma of the head and neck with high-risk pathologic features was analyzed in RTOG 0234 randomized phase II clinical trial. The high-risk factors are extracapsular nodal extension, positive surgical margins and two or more metastatic lymph nodes. In this study, 203 analyzable patients (including 21 patients with advanced laryngeal cancer) were randomly assigned to 60 Gy radiation with Cetuximab once per week plus either Cisplatin 30 mg/m2 or Docetaxel 15 mg/m2 once per week. The Docetaxel regimen shows favorable outcome with improved 2-year disease-free survival (DFS 66% against 57% for Cisplatin arm) and overall survival (OS 79% against 69% for Cisplatin arm), with decreased hematologic toxicity (grade 3 to 4 myelosuppression in 14% of patients versus 28% for cisplatin arm). In conclusion, the delivery of postoperative chemo-radiotherapy (using Cisplatin or Docetaxel once per week plus 60 Gy radiation) with concurrent once per week Cetuximab is feasible and tolerated with predictable toxicity(35).
The interval between surgery and adjuvant radiotherapy
The time between surgery and adjuvant radiotherapy (normally, 4-6 weeks), necessary for postoperative wound healing, may allow the proliferation of residual tumor cells because of the growth factor increased concentrations in surgical bed(36). The postoperative recovery interval is also an opportunity for tumor cells to become radiation refractory, because resistance is proportional to the number of surviving cells(37).
To evaluate the practical possibility of an early postoperative chemotherapy, 70 resected patients with locally-advanced stages III to IV head and neck squamous carcinoma (positive surgical margins and/or extracapsular nodal extension and/ or multiple positive nodes) are treated in the RTOG 0024 trial by 3 early chemotherapy cycles followed by concurrent chemoradiotherapy. Early-adjuvant chemotherapy consists of Paclitaxel 80 mg/m2 for three weekly cycles starting from the first or second week after surgery (i.e., postoperative day 7 through 14). Concurrent chemotherapy was Paclitaxel 30 mg/m2 i.v. followed immediately by Cisplatin 20 mg/m2 i.v. once weekly for three cycles (i.e., cycles 4 through 6) given in the last 3 weeks of radiotherapy (60 Gy in 30 fractions). The fourth grade non hematologic toxicity produced by the early-adjuvant chemotherapy is represented by mucosal and cutaneous fistulae (3 patients), mucositis (2 patients), and superficial skin dehiscence (3 patients). After adjustment for the prognostic factors, the regimen in RTOG 0024 may be superior to either adjuvant radiotherapy or to radiotherapy with concurrent chemotherapy, with an estimated reduction in risk for disease-free survival and death of approximately 30% to 40%. The locoregional control benefit is greater, with estimated reductions in risk of 41% versus chemo-radiotherapy and 60% versus radiotherapy alone(38).
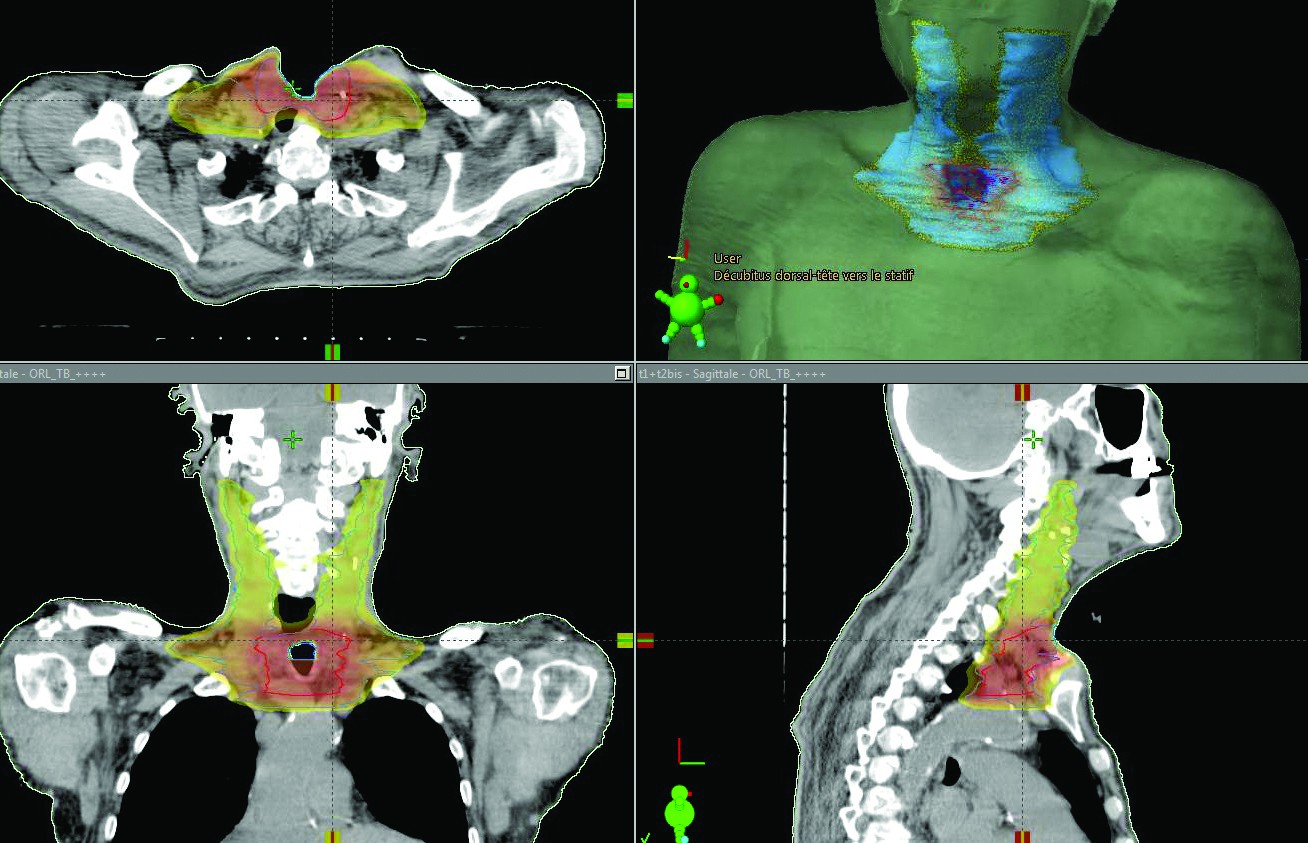
Conclusions and recommendations regardind post laryngectomy adjuvant treaments
For each patient, a multidisciplinary treatment schedule should be established. The patient’s nutritional status must be corrected and maintained, and dental rehabilitation is indicated before radiotherapy(39).
The 2016 guideline of National Comprehensive Cancer Network (NCCN) recommends adjuvant concurrent chemoradiation therapy for significant nodal disease (multiple positive neck nodes-N2-N3, extracapsular extension) and/or large and infiltrative pT4 tumors. Postoperative exclusive radiotherapy is indicated if any two of the following factors are present: close surgery margins (<5 mm), 1 positive lymph node, multicentric primary or peri-neural invasion. The adjuvant radiotherapy is preferable to begin before 6 weeks after surgery and to deliver 60-66 Gy in 2 Gy/fraction to nodal and laryngeal area that are at risk for local/regional recurrence(40).
The recommended adjuvant chemo-radiotherapy regimen uses Cisplatin 100 mg/m2 administered every 21 days for three cycles (days 1, 22, and 43) concurrently with standard doses of conventionally fractionated radiotherapy(41).
Laryngeal cancer